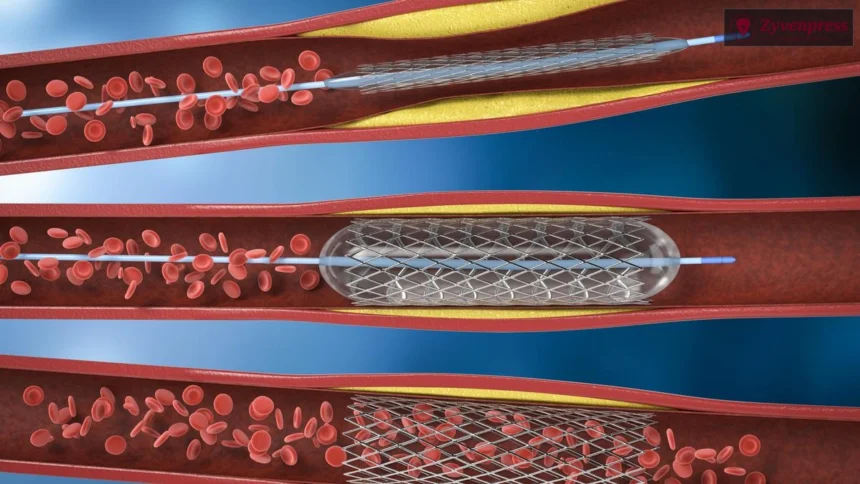
The landscape of modern cardiovascular medicine has experienced a profound shift over recent decades, largely driven by technological advancements in catheterization laboratories. Percutaneous Coronary Intervention (PCI), encompassing balloon angioplasty and the deployment of tiny mesh tubes known as stents, has transformed how physicians manage blocked arteries. Yet, recent political commentary questioning the necessity of certain elective procedures has ignited a fierce debate within medical circles, highlighting a delicate tension between clinical necessity, public trust, and procedural economics.
To understand the controversy, experts emphasize a vital boundary: the clinical context in which a procedure occurs. During a sudden, acute myocardial infarction—commonly known as a heart attack—a coronary artery becomes abruptly blocked. In these terrifying emergencies, timely angioplasty restores vital blood flow, preserves healthy heart muscle, and drastically improves survival rates. Under such critical circumstances, second opinions are entirely redundant, as swift action remains the ultimate priority. Similarly, carefully selected patients suffering from severe, persistent chest pain that limits daily activities often find substantial relief through these interventions.
The Anatomy of a Misconception
However, a significant clinical gulf separates emergency life-saving interventions from elective procedures prompted merely by the visualization of a narrowing vessel on an angiogram. Medical professionals point out that a standard coronary angiogram maps out the physical architecture of blood vessels, but it does not automatically prove that a specific blockage requires mechanical intervention. Deciding whether to deploy a stent demands a comprehensive evaluation incorporating patient symptoms, the functional severity of the blockage, overall coronary patterns, and anticipated clinical benefits.
“A coronary angiogram shows the anatomy of the arteries; it does not, by itself, establish that a narrowing requires intervention.”
This nuanced perspective gains robust backing from landmark clinical investigations. Published in the New England Journal of Medicine, the extensive ISCHEMIA trial evaluated over 5,000 patients across multiple global sites who suffered from stable coronary artery disease and moderate-to-severe restricted blood flow. Participants were split into two groups: one receiving an initial invasive strategy involving angiography and subsequent revascularization, and the other treated conservatively with optimal medical management. After years of careful monitoring, researchers found virtually no significant statistical difference between the two cohorts regarding major cardiac events, hospitalizations, or overall mortality. The core takeaway is clear: for stable patients, rigorous medical therapy achieves outcomes comparable to invasive procedures.
Diverging Trends and Economic Realities
Despite such evidence, procedural volumes continue to display fascinating global divergences. Data from national councils highlights a dramatic trajectory in India, where annual PCI procedures skyrocketed more than sixfold over a sixteen-year span. Conversely, regions like the United States observed a notable contraction in similar interventions during a comparable timeframe, driven heavily by enhanced preventive care and stricter adherence to pharmacological management guidelines.
Analysts caution against drawing simplistic conclusions from these divergent numbers. India’s steep climb must be contextualized within its massive population, significant burden of premature heart disease, rising socio-economic standards, and rapidly expanding access to modern cardiac facilities. Nonetheless, the trend forces a critical examination of practice patterns, institutional incentives, and potential knowledge gaps regarding the true efficacy of non-invasive therapies.
The Foundation of Long-Term Care
Medical experts continually stress that evidence-based medical therapy remains the undisputed cornerstone of cardiovascular care. Comprehensive regimens typically involve targeted cholesterol reduction, precise blood-pressure control, advanced diabetes management, anti-platelet medications, and sustainable lifestyle modifications. A mechanical stent merely props open a localized narrowing; it fails to reverse systemic atherosclerosis or eliminate the ongoing vulnerability to blockages elsewhere in the vascular network.
As the medical community navigates these turbulent discussions, the ideal path forward rejects both blanket condemnation of interventional cardiologists and blind faith in every procedural recommendation. Most healthcare practitioners consistently prioritize their patients’ welfare, yet vigilance against inappropriate practice remains essential. Ultimately, the true measure of a healthcare system lies not in the sheer volume of operations executed, but in the preservation of lives through timely, affordable, and righteous care.